Psychological strategies and dizziness-specific exercises.
These are recommended, but specifically for people identified as medium or high risk of a poor recovery, not as a default addition for everyone 3.
The car in front stopped and you didn't have enough road. At the scene you felt shaken but basically fine: you swapped details, you drove home. It's the next morning, or the one after that, when your neck won't turn far enough to check a blind spot and your head has started aching from the base of your skull.
That delay is the most misread thing about this injury. Whiplash symptoms can be absent at first and take several hours, or even days, to show up 1. It isn't evidence that something is quietly getting worse, and some pain and discomfort along the way is a normal part of recovering 2.
The damage happens in well under a second, and it isn't one movement. Your neck goes through a sequence: it's first compressed from below into an abnormal S-shape (lower segments bent backwards while the upper segments are bent forwards), then the upper segments extend too, before the head and neck are swept forwards. Along the way the small joint capsules at the back of the spine are strained beyond their normal limits 10.
Those joints, and the muscles and ligaments around them, are what's actually sore. That's why the pain shows up as stiffness, tenderness and a neck that won't turn, not anything dramatic. It also explains the delay: nothing has to swell immediately for the injury to have happened 1.
The consequences worth taking seriously aren't in the first 48 hours anyway. Complications of whiplash can include chronic pain, depression and post-traumatic stress symptoms 1, which is the real argument for addressing it properly instead of waiting to see.
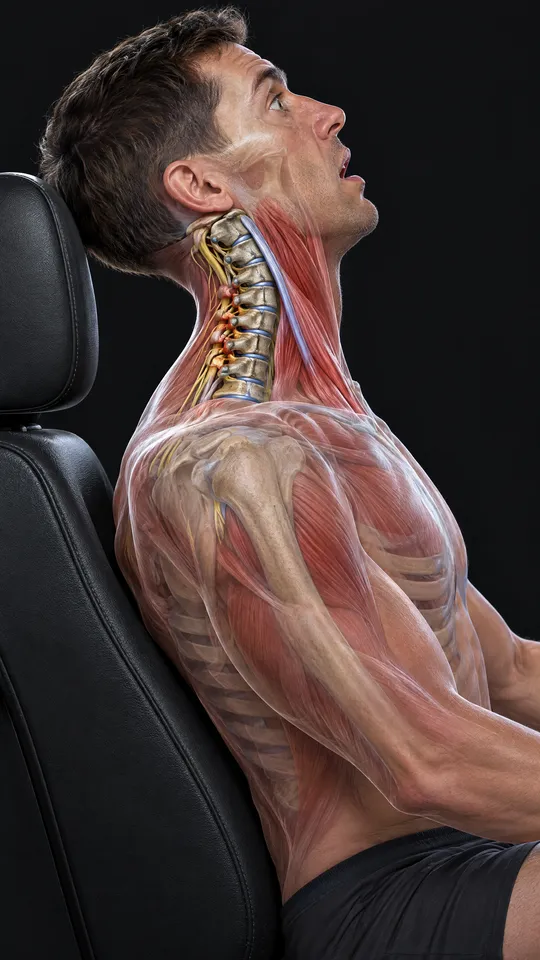
People ask about "the four stages of whiplash", and the answer is slightly different from the question: two separate things get described with the same word.
The three stages are the biomechanical ones above: what your neck physically does during the impact 10. What people usually want is the severity scale. That's the Quebec Task Force classification, running from 0 to IV, and it's the system the Australian Physiotherapy Association recommends clinicians use 3,4:
The classification is still the one current Australian recommendations use 3. The practical point: grades 1 and 2 cover the large majority of what walks through a physiotherapy door, and they're managed with advice and exercise, not anything invasive. Grades 3 and 4 need medical assessment first. See the red flags further down.
Whiplash is diagnosed by examination, and scans usually aren't needed 1. A doctor checks for pain, stiffness and tenderness, tests nerve signs such as your reflexes and muscle strength, checks for broken bones or dislocations, and asks about headaches, your daily activities and whether your driving is affected 1.
To screen for a fracture in the neck, clinicians are advised to use a checklist called the Canadian C-spine rule 3. After that, how far your neck moves and where it's tender to press sort out the milder grades, and nerve tests pick up the grade where a nerve is involved 3. Expect your pain and neck-related disability to be measured again at regular intervals, to see whether treatment is working 3.
We start by telling you what's actually going on. Accurate advice is a frontline treatment recommendation in its own right 3, not the preamble before the real thing. As for how strong that effect is: one systematic review found that in acute whiplash a simple oral education session is enough, and adds that more research is needed on its format 11. We'd rather tell you that than pretend the hands-on part does all the work.
Neck-specific exercise is the main intervention. It's a frontline recommendation 3, and the exercises are very gentle, typically about ten minutes a day 2. Our Exercise Prescription and Conditioning approach is how that gets built and progressed. Two notes from the evidence: the pooled benefit of guided neck-specific exercise is real but small, and not every trial found a significant effect 5; and it shows up mainly in programs running past six weeks at two or more sessions a week 5. Worth doing, worth doing consistently. Not a switch that flips.
Hands-on treatment, alongside the exercise, not instead of it. Physiotherapists commonly combine exercise-based treatment with manual therapy to improve neck movement and reduce pain 1. Our Manual Therapy page covers what that involves.
We screen your recovery risk early. Current recommendations include a validated tool (WhipPredict or the Short Form Örebro) to identify who's at higher risk of a poor recovery 3. That cuts both ways: medium and high risk means extra strategies added, low risk means not being overtreated, because overtreatment can complicate recovery 3. Being sent away with less is sometimes the correct clinical answer.
We keep you working and moving, with the load adjusted. Continue normal activities as much as you can 1. Practical swaps from NSW's own injury guidance: carry on the other side, make more trips with less, change position often, spread tasks across days, use a step ladder instead of reaching overhead 2.
If the accident was on a NSW road, your physiotherapy may be claimable through CTP. Ahmed is a SIRA-registered provider (registration 22498). SIRA is the same NSW regulator that publishes the state's whiplash recovery guidance. Our WorkCover & CTP Physiotherapy page sets out how claims work.
These are recommended, but specifically for people identified as medium or high risk of a poor recovery, not as a default addition for everyone 3.
An Australian placebo-controlled trial of 80 people with chronic whiplash, followed for 12 months, found dry needling with exercise had no clinically worthwhile effects over sham needling with exercise, and no effect on how recovered people rated themselves 6. We offer Dry Needling and it has its uses elsewhere. For chronic whiplash specifically, the evidence doesn't support it, and we'd rather say so.
Simple medications are part of the standard recommendations 1,3, taken on the advice of your doctor or pharmacist 1. Physiotherapists don't prescribe or administer medication. That conversation belongs with your GP or pharmacist.
Soft collars: guidelines don't recommend them 4, and in one trial early exercise beat collar therapy for pain and disability 9. Advanced imaging when the findings are pain and musculoskeletal signs only 3. Surgery and injections, which are not recommended 3.
Whiplash treatment here follows The Well Motion Recovery Path™. You move up a phase when your neck can do more, not when a set number of weeks has passed.
How long it usually takes. Most people recover within a few days or weeks, and some take several months 1,2. About half of Australians recover rapidly and the other half may develop longer-term pain 3, so we cannot give you a date.
You can't control the driver behind you. You can control your seat, and that's where the evidence is:
Get urgent medical care after an accident if you have any of these 1:
Those need a doctor before they need a physiotherapist.
Numbness, weakness or pins and needles in your arms, shoulders or legs: call us the same day.
Otherwise, book an assessment instead of pushing on alone if the pain isn't easing over the first few weeks, if you're avoiding driving, if the headaches have become the main problem, or if your mood and sleep have gone with it. Chronic pain, depression and post-traumatic stress symptoms are recognised complications 1, and they're much easier to head off than to unwind later. If your neck pain has already outlasted the accident by months, our Neck Pain page is the better starting point.
If your neck is painful and stiff after an accident, it's after hours, a weekend or a public holiday, and you have none of the urgent signs above, our after-hours emergency physiotherapy can come to you. Call (02) 8111 5633.
For most people, none of that happens. Whiplash is a recoverable injury, and what helps most is unglamorous: keep moving, keep working where you can, do the ten minutes.
We start by listening: how it began, what makes it worse, and what it's stopping you from doing. Then we examine the area, explain what we find in plain English, and agree a plan with you. Your first visit is 40 minutes at Engadine and 30 minutes at our other clinics.
We see patients at Engadine, Mount Annan, Narellan and Appin, and at home through our mobile physiotherapy service. If you have private health cover, here's how health fund rebates work for physiotherapy.
Don't wear a soft collar: guidelines don't recommend them 4, and early exercise has beaten collar therapy for pain and disability 9. Don't stop work entirely if there's any version of it you can still do 2. Don't push for advanced imaging when the findings are pain and musculoskeletal signs only 3. And don't assume more treatment means faster recovery: low-risk patients shouldn't be overtreated, because it can complicate recovery 3. Surgery and injections aren't recommended for whiplash either 3.
We'd rather give you a straight answer than a confident-sounding one. The sources behind this page don't specify a sleeping position, so we won't attach a citation to a claim they don't make. What they do support is the principle underneath the question: change position often 2, keep the neck moving within comfort, and raise night pain at an assessment so the advice can be matched to your neck rather than to a generic one.
Most people recover within a few days or weeks; some take several months 1,2. The part that's less often said: about half of Australians recover rapidly, and the other half may develop long-term pain, disability and psychological distress 3. As for the physiotherapy itself, the exercise evidence points to programs running longer than six weeks at two or more sessions a week 5, so plan in months, not appointments.
Yes, with a caveat we'd rather state than hide. Exercise-based treatment, sometimes combined with manual therapy, is standard Australian advice for whiplash 1, and neck-specific exercise is a frontline recommendation 3. But pooled evidence from eleven randomised trials puts the benefit of guided neck-specific exercise over comparison programs at statistically significant and small (neck pain SMD −0.25; disability SMD −0.35), with not every trial finding a significant effect 5. It helps. It isn't a cure, and anyone promising you one is overselling.
Usually. Full recovery commonly happens somewhere between a few days and several weeks 1,2. It isn't universal, though: roughly half of people go on to longer-term pain and disability 3, and your own risk of a slow recovery can be screened for early with a validated tool 3. That's the reason to treat it properly early, not a reason to panic.
Usually there's nothing to see, and that's the expected result, not a disappointing one. In most cases x-rays and other tests aren't needed 1,2. A doctor may arrange imaging if a broken bone or spinal cord injury is suspected, and advanced imaging is reserved for a suspected pinched nerve rather than pain and musculoskeletal signs alone 1,3. A clear scan doesn't mean nothing is wrong; it means the injury is the kind scans don't show, which is the kind that responds to exercise and advice.
Stiff, aching, recurring neck pain that builds through the day at a desk or on the tools.
Read moreYou've woken with your head stuck tilted to one side, and a spasm that won't let you straighten it. Infants too.
Read morePain, numbness, tingling or weakness travelling from your neck down into your shoulder, arm or hand.
Read moreArm symptoms coming from compression in the narrow space between your neck and shoulder, often worse overhead.
Read moreA headache that starts in the neck joints and muscles rather than in your head.
Read moreAching at the base of your neck and between your shoulder blades after hours looking down at a screen.
Read more
How would you like to reach us?
Message us on WhatsAppFor bookings and enquiries. Please don't send medical details. Call (02) 8111 5633Request a call-back
Request sent
Thank you. We'll call you back on the number you gave us.
This is a preview, so nothing was actually sent.